


AHA ACLS
Massachusetts General Hospital IS
- 3.4
- 39.00 Reviews
- 50.00K
- Downloads
- Free
- Price
Screenshots

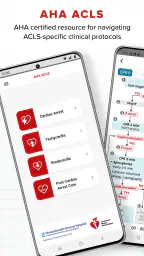
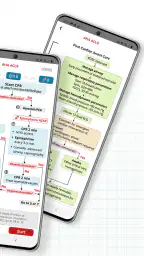
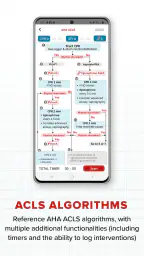

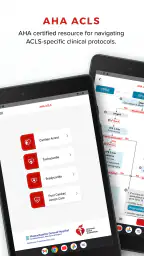

AHA ACLS Pros and Cons
Pros
- Follows current AHA ACLS algorithms and emergency care priorities.
- Includes practical guidance for cardiac arrest and peri-arrest situations.
- Useful reference for healthcare students, nurses, and clinical teams.
- Helps reinforce medication choices, rhythms, and treatment sequences.
- Official AHA content increases confidence in the information provided.
Cons
- Most valuable features may require payment or an active subscription.
- Content can feel advanced for users without medical training.
- Guidelines may change, requiring regular updates to stay current.
- Not a substitute for hands-on ACLS certification or instructor guidance.
- Some sections may depend on internet access or account registration.
 Analysis by All-app
When a cardiac emergency becomes chaotic, the hardest part is often not knowing that a protocol exists. It is finding the right step quickly, keeping the sequence straight, and communicating clearly while several people are working at once. That is the problem AHA ACLS tries to address. I found it most useful as a compact reference and practice companion for clinicians, students, and responders who need to review advanced cardiovascular life support pathways without opening a textbook.
This is a medical app from Massachusetts General Hospital IS, aimed at an Everyone audience, although its subject matter is clearly more relevant to people with clinical training. It is free to install, with optional in-app purchases priced at $3.99 per item. The app has passed the fifty-thousand-install mark and holds a 3.4 average from 162 ratings, so it has a noticeable user base but also a mixed reception. That combination matches my impression: the core idea is practical, but the experience depends heavily on what you expect from it.
From an uncertain emergency to a usable protocol
I find the most useful starting point is to treat uncertainty as a cue to pause and identify the decision that needs review, rather than to browse broadly during a busy moment. A short, focused rehearsal can make the next step easier to explain and hand off. From there, I look at how the app’s protocol flow holds up when attention is divided.
Starting with the right kind of problem
I would not treat this as a general first-aid app or as a substitute for formal ACLS training. Its value begins when the user already understands the basic language of resuscitation and wants a faster way to orient themselves around ACLS algorithms. The store summary describes an ACLS code runner and protocols, and that focus is important. This is not designed to teach every underlying cardiac concept from the beginning; it is designed to help users work through structured emergency decisions.
That makes the starting condition very specific. A learner may be preparing for a course, a clinician may be refreshing an algorithm before a shift, or a team member may want a quick mental rehearsal of how a code should progress. In each case, the useful question is not simply “What is ACLS?” but “What should I check next, and how do I keep the response organized?”
Before relying on it, I would make sure I already knew the local emergency procedures, medication policies, equipment layout, and scope of practice. Protocol references can support decision-making, but they do not replace the team leader, current institutional guidance, or real-time clinical judgment. In a live event, the app should be secondary to patient assessment and direct communication.
Getting oriented without turning the phone into the team leader
The first practical advantage is concentration. A printed manual can be comprehensive, but it is slower to scan when I only need to confirm the branch of an algorithm. A phone-based reference is easier to keep nearby, especially during study or a quick review before a simulation. The trade-off is that a small screen can encourage users to look down at the wrong moment, so I see the app as something to consult between actions rather than something one person should stare at throughout an active code.
More Reads From Our News Desk

Switching to the Xbox App: What Changes in Your Gaming Routine

Coloring & Learn Review: A Satisfying Canvas, Cluttered Menus

Microsoft 365 Copilot on Your Phone: Who Actually Needs It?

Mafia City: The Crime Saga That Outshines Its Rivals

Woodturning Transformed: How OS Updates Enhance Your Craft

How Tiles Hop EDM Rush Redefines Music Gaming
For study, I recommend approaching it with a question already in mind. For example, I might review how the response changes when a rhythm is shockable, or what information needs to be passed when a new team member takes over. That approach turns the app into an active rehearsal tool instead of passive scrolling. It also exposes gaps in memory more effectively than rereading a long chapter.
A useful habit is to say the decision pathway aloud after checking it. I can close the screen and explain the sequence from memory, then reopen the relevant protocol to verify the parts I missed. This creates a simple input-to-outcome loop: identify the situation, follow the pathway, explain the next action, and check whether the explanation remains coherent without the screen.
Following the step-by-step flow
The central workflow is built around protocols rather than broad medical articles. I start by identifying the clinical situation, move through the displayed decision points, and use the resulting pathway as a prompt for what the team should assess or do next. That structure is particularly helpful for learners who know individual interventions but lose track of their order under pressure.
What I like about this format is that it encourages sequence awareness. In ACLS, a correct action at the wrong time can still create confusion. A protocol view keeps attention on assessment, rhythm-related decisions, intervention, reassessment, and the next branch. Even when I already know the material, seeing the pathway laid out helps me notice where a handoff or reassessment belongs.
However, an algorithm on a screen can look more definitive than it really is. Real patients do not always fit a clean branch. A rhythm may change, information may be incomplete, or the team may be dealing with reversible causes that do not appear in the order a learner expects. I would therefore use the app to reinforce structured thinking, not to encourage mechanical button pressing.
One of the more useful study techniques is to run the same protocol twice with different roles in mind. The first pass can be from the team leader’s perspective: what must be recognized and announced? The second can be from the compressor, medication nurse, monitor operator, or recorder’s perspective: what information must that person hear and repeat? This reveals a practical weakness in many study sessions: people memorize the clinical sequence but do not rehearse how the sequence is communicated.
Using the code-runner idea for rehearsal
The code-runner portion is most valuable when I treat it as a controlled simulation rather than a game. I can begin with the initial situation, make a decision, and observe how the next stage of the protocol is framed. The benefit is not entertainment; it is the chance to practice maintaining order while the scenario changes.
For a student, I would use short sessions and repeat the same scenario until the reasoning becomes verbal and automatic. Afterward, I would write down three things: the first assessment I overlooked, the point where I hesitated, and the information I would need to hand over. That small review turns a quick interaction into a study record without pretending that an app can reproduce the noise and pressure of a real resuscitation.
For an experienced clinician, the app may be better as a refresher than as a complete training environment. It can help bring an algorithm back to the front of memory, but it cannot reproduce equipment handling, team dynamics, physical fatigue, closed-loop communication, or the consequences of delayed action. Those skills still require simulation, supervised practice, and local training.
Making handoffs part of the workflow
The strongest way to use this app is to connect every protocol step with a spoken handoff. If I am reviewing a scenario alone, I can pause and summarize the patient state, the rhythm or response being considered, the intervention already completed, and the next reassessment point. That mirrors what a real team needs when someone joins or replaces another responder.
This is also where the app’s compact format can be both helpful and limited. It can remind me of the clinical pathway, but I still have to translate that pathway into a clear message. A useful handoff should not sound like someone reading a screen. It should tell the incoming person what has happened, what is happening now, what has been ruled out or remains uncertain, and what should be watched next.
I would especially recommend using the app to rehearse transitions. Start with one person leading, then imagine a handoff after a rhythm check, after an intervention, or when the team becomes larger. Ask yourself what information must survive the transition. This is a less obvious use than simply memorizing protocols, but it is one of the best ways to turn reference material into team-ready behavior.
Another practical tip is to separate clinical content from local logistics. The app can support the first part, while your workplace procedures determine who calls for help, where equipment comes from, how medications are prepared, and how documentation is completed. Mixing those layers can create false confidence, especially for new users who assume a general protocol maps perfectly onto their department.
What outcome the app can realistically deliver
The realistic outcome is improved familiarity with ACLS decision pathways and a quicker way to revisit them. I would expect a learner to finish a session with a clearer sense of what comes next, where reassessment belongs, and which points deserve verbal confirmation. That is a worthwhile result, particularly when the alternative is searching through scattered notes or relying on memory alone.
It can also make study more targeted. Instead of rereading every topic, I can focus on the branch that caused hesitation and repeat it until the sequence is easier to explain. The app’s value grows when it is used alongside a course, a current manual, or supervised simulation. On its own, it is more of a structured reminder than a full educational program.
I would not use a successful run in the app as proof of clinical readiness. A smooth digital sequence does not show whether someone can recognize a deteriorating patient, perform high-quality practical interventions, communicate under stress, or adapt when the situation does not match the expected pathway. The best result is modest but useful: better preparation, not certification by itself.
Where the flow breaks
The first point of friction is the gap between a clean protocol and a messy emergency. Apps are good at presenting ordered decisions; they are less good at representing incomplete information, interruptions, simultaneous tasks, and competing priorities. If a user expects the code runner to behave like a full simulator, disappointment is likely.
The second issue is audience fit. The Everyone age label makes the app broadly accessible, but the subject is not really beginner-friendly in the same way as a wellness tracker or basic first-aid guide. Someone without medical training may recognize familiar terms without understanding the clinical responsibility behind them. I would skip it as a standalone resource if I were looking for introductory emergency education.
There is also a difference between a quick reference and an authoritative source. Clinical recommendations can change, and local practice may add requirements. I would check the current training materials used by my employer or course before treating any protocol reference as the final word. For a high-stakes decision, the app should support—not replace—qualified guidance and institutional policy.
The mixed rating is worth keeping in mind. The app is not universally loved, and that may reflect differences in expectations as much as differences in usefulness. People wanting a fast ACLS refresher may appreciate its focused design, while users expecting detailed explanations, rich simulation, or a complete course may find it too limited. I would judge it by the narrower job it performs.
How it compares with the usual alternatives
Compared with a paper handbook, AHA ACLS is easier to carry and quicker to consult when I want a particular pathway. A handbook usually wins for extended reading, background explanations, and comfortable side-by-side comparison of topics. I would use the app for rapid orientation and the book or course material for deeper study.
Compared with a general medical reference app, this one is more focused on ACLS workflows. A broad reference may offer wider coverage, but that breadth can make it slower to reach the exact decision pathway I need. If my goal is medication information across many specialties, a general clinical reference would probably be the better choice. If my goal is rehearsing ACLS structure, the narrower focus is an advantage.
Compared with a full simulation platform, the app is lighter and more convenient but less immersive. A simulation platform is better for teamwork, timing, equipment use, and realistic pressure. AHA ACLS is better suited to the moments before or after that training, when I want to review the logic and identify where I became uncertain.
The optional purchases also affect how I would evaluate it. The basic free entry makes it reasonable to test whether the workflow fits my study habits before spending anything. I would only consider an individual purchase after identifying a specific gap the added material addresses, rather than assuming that paying automatically turns the app into a complete course.
Who should use it and who should pass
I think it is a sensible companion for healthcare students, clinicians refreshing ACLS knowledge, and responders preparing for structured practice. It is especially suitable for someone who already knows the terminology and wants to rehearse decisions in a compact format. The current version is 3.2.0 and supports devices running iOS or Android 8.0 and later, which keeps it accessible on many older phones.
I would pass if I wanted a beginner’s guide to recognizing emergencies, a replacement for hands-on certification, or a comprehensive clinical reference covering every cardiac and emergency-care topic. I would also hesitate if my workplace requires a particular official digital resource and does not allow informal references during clinical work. In that situation, local policy matters more than convenience.
My final recommendation after following the workflow
After using it as a starting-condition-to-outcome tool, I see AHA ACLS as a focused study and reference aid rather than a complete emergency-training solution. Its best quality is the way it puts protocol thinking into a form that is easier to revisit, rehearse, and connect with handoffs. Its main weakness is the same thing: a compact digital pathway cannot capture all the uncertainty and teamwork of a real code.
My recommendation is to use it deliberately, not blindly. Open it before training to refresh a pathway, run through a scenario while speaking the handoff aloud, then compare your understanding with current course or workplace guidance. Used that way, it can make ACLS review more organized and expose gaps before they matter. Used as the only source of preparation, it is not enough.
For a free medical app with optional $3.99 purchases, it is worth trying if ACLS is already part of your responsibilities or studies. I would keep it as a pocket refresher, pair it with authoritative training, and avoid consulting it in a way that distracts from direct patient care. That is where it fits best: between formal learning and real-world readiness, helping me remember the route without pretending to drive the emergency response.
In short, AHA ACLS is most convincing when the user needs a structured reminder, a rehearsal prompt, or a way to examine how decisions and handoffs fit together. It is less convincing as a standalone teacher. Knowing that distinction makes the app much more useful and prevents the most important mistake: confusing familiarity with a protocol for complete preparedness.
Frequently Asked Questions
What is AHA ACLS, and who is it designed for?
AHA ACLS refers to Advanced Cardiovascular Life Support training based on American Heart Association guidelines. It is primarily intended for healthcare professionals and students who may respond to cardiac arrest, stroke, acute coronary syndrome, and other cardiovascular emergencies. The app can be useful for reviewing algorithms, medications, rhythm recognition, and emergency procedures, but it does not replace an official course, instructor-led practice, or current workplace protocols.
Can I use the AHA ACLS app to become officially certified?
The app should generally be treated as a study and reference tool rather than a complete certification program. Official ACLS certification normally requires registration with an authorized American Heart Association training center, completion of the required learning activities, and successful skills and written assessments. Before relying on the app for certification preparation, check its current content, publisher information, and whether it is connected to an approved training provider in your country.
What topics and learning materials are included in AHA ACLS?
Depending on the version, AHA ACLS may provide access to resuscitation algorithms, cardiac arrest management steps, ECG rhythm practice, drug information, dosage references, case-based questions, and quick-review material. These resources can help users revise important concepts before a course or exam. Because medical recommendations and app features may change, users should confirm that the content reflects the latest AHA guidelines and local clinical requirements.
Is AHA ACLS suitable for beginners or only experienced medical professionals?
The app may be helpful for both learners and experienced clinicians, but the amount of benefit depends on the user’s background. Beginners may use it to become familiar with terminology and treatment sequences, while trained professionals can use it for revision and self-testing. However, ACLS involves practical skills, teamwork, communication, and clinical judgment, so beginners should not rely on the app alone when learning how to manage real emergencies.
Can the information in AHA ACLS be used during a real medical emergency?
AHA ACLS may offer convenient access to important reference material, but it should not be considered a substitute for emergency services, trained personnel, or institutional protocols. In a real emergency, contact local emergency services and follow the procedures for your setting. Healthcare professionals should use current official guidelines and approved clinical resources, since app content may be incomplete, outdated, or unsuitable for a particular patient or healthcare system.


